

FASD coordination services service delivery process
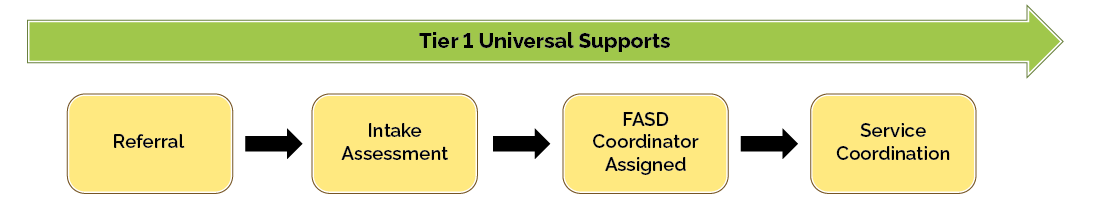
1. Referral
Families/support networks and local cross-sector partners may self-initiate access to Tier 1 educational and training materials. Information on how to access Tier 1 services should be made publicly available.
A referral and formal intake process is optional for Tier 1 services and required for Tier 2 and Tier 3 services.
Referrals may be made at any point for a child/youth who is or may be living with FASD and their family/support network. Families/support networks may also self-refer by phoning their local Coordinating Agency and requesting support.
When a local cross-sector partner identifies that a family/support network may benefit from FASD Coordination Services, they should explain what FASD Coordination Services are and why they may be helpful. If the family/support network is interested, and with their consent, the referring partner should share information with the Coordinating Agency to support intake to FASD Coordination Services through a warm referral.
With appropriate consent, referrals should include information about the child/youth and their family/support network to reduce the need for families/support networks to repeat their story. At a minimum, referrals should include:
- Basic information about the family/support network (e.g., names and contact information);
- Information about the family/support network’s strengths, needs, and circumstances, including whether they would like to pursue an FASD diagnosis for their child/youth; and
- Information about the child/youth’s strengths, needs, and services they are currently accessing or waiting to access.
Referrals to FASD Coordination Services may be made in parallel with referrals to other services. Referral to FASD Coordination Services does not prevent a family/support network from accessing other appropriate, available community services for which they are eligible, as FASD Coordination Services do not provide direct therapy, clinical supports, or respite.
2. Intake and assessment
Following a referral, the Coordinating Agency will implement an equitable and culturally safer intake process that enables an FASD Coordinator to work collaboratively with the family/support network to assess their needs and goals and determine whether or not Tier 2 or Tier 3 FASD Coordination Services are appropriate.
Families/support networks may move between Tier 2 and Tier 3 services as their needs change over time. FASD Coordinators will support families/support networks through these transitions while ensuring continuity and responsiveness in service delivery.
Eligible children/youth who are or may be living with FASD and who have more complex needs may be referred to CSP for ongoing service coordination and goal setting. In these cases, the CSP Service Planning Coordinator becomes responsible for service coordination and performance measurement reporting for the child/youth and their family/support network. FASD Coordinators may continue to be involved; however, this support is provided through Tier 1 and/or Tier 2 FASD Coordination Services.
3. Assigning an FASD coordinator
Once a family/support network has been identified as requiring Tier 2 or Tier 3 FASD Coordination Services, they will be assigned an FASD Coordinator. The assigned FASD Coordinator may or may not be the same FASD Coordinator who conducted the intake process.
By the time a family/support network is ready to begin goal setting, an FASD Coordinator must be formally assigned. Assignment decisions should consider:
- Family/support network preferences;
- Existing relationships;
- The family/support network’s assessed needs, including whether specific experience or expertise is required; and
- Other relevant factors, such as linguistic or cultural needs.
Families/support networks should be clearly informed of who their assigned FASD Coordinator is, the role of the FASD Coordinator, and that the FASD Coordinator is their primary point of contact.
4. FASD service coordination
Developing an FASD Service Plan (Appendix B) is required for families/support networks accessing Tier 3 FASD Coordination Services and is optional for families/support networks accessing Tier 2 FASD Coordination Services.
a. Family/Support network strengths and needs are identified
Once a family/support network has completed the referral and intake process and has been assigned an FASD Coordinator, the FASD Coordinator will work collaboratively with the family/support network to identify their strengths and needs.
Children/youth and their family/support network are at the centre of FASD Coordination Services. When an FASD Service Plan is initiated, the FASD Coordinator will gather key information about the child/youth and their family/support network through:
- Discussion with the child/youth and their family/support network;
- Information shared by other local cross-sector partners; and
- Conducting a strengths and needs assessment.
A strengths-based approach is used to inform the development of the FASD Service Plan, including identifying areas where children/youth and their family/support network demonstrate strengths, as well as areas where additional support may be beneficial. Strengths may include functional strengths such as behaviour regulation or problem-solving skills, as well as family/support network, cultural, and community strengths, such as the involvement of extended family members. A family/support network’s connections to cultural communities, including First Nations, Métis, Inuit, and Urban Indigenous communities, should be identified as part of the strengths assessment to inform service planning.
Family/support network strengths and needs should be monitored and updated at regular intervals. As strengths and needs evolve over time, the intensity at which FASD Coordination Services are delivered may be adjusted accordingly.
FASD Coordinators will also provide families/support networks with knowledge and skills to support their child/youth more effectively by offering resources and ongoing support. They should also ensure that families/support networks understand the FASD diagnostic process.
Decisions regarding the frequency of engagement with an FASD Coordinator and the review and updating of the FASD Service Plan are made collaboratively by the child/youth and their family/support network, in partnership with the FASD Coordinator, and informed by the family/support network’s strengths, needs, and capacity.
b. Goal setting and prioritization
The family/support network’s circumstances, preferences, and knowledge of their child/youth and goals form the foundation of service planning. The child/youth’s voice, preferences, and goals are also central to FASD Coordination Services, particularly as they mature and begin preparing for adulthood.
Goal setting is founded on the F-words for child development (Function, Family, Fitness, Fun, Friends, and Future) and based on what the child/youth and their family/support network see as most important. Goals may relate to obtaining an FASD diagnosis, participation in specific activities, access to therapies, or other domains of development. Goals may also be prioritized based on urgency or changing family/support network circumstances. Initial goal setting is completed collaboratively by the child/youth and their family/support network with the support of the FASD Coordinator. Families/support networks and/or the child/youth have the final decision regarding which goals are included in the FASD Service Plan.
Obtaining an FASD diagnosis
Although obtaining a formal diagnosis is not always possible, and therefore not required to access FASD Coordination Services, it can be a helpful step in understanding a child/youth’s unique strengths and needs. For families seeking an FASD diagnosis, FASD Coordinators play a critical role in supporting families/support networks through the FASD diagnostic process. This includes sharing information about the diagnostic process and facilitating referrals to FASD diagnostic clinics, where and when available.
Recognizing that access to diagnostic services varies significantly across communities, in communities where diagnostic services are not available or are limited, FASD Coordinators are expected to assist families/support networks in navigating alternative diagnostic pathways within their community. This may include working with Children’s Treatment Centres (CTCs) to access FASD-informed assessments, engaging with child welfare partners to support confirmation of prenatal alcohol exposure, or strengthening collaboration among local cross-sector partners to support families/support networks in pursuing an FASD diagnosis.
When a child/youth and/or their family/support network informs an FASD Coordinator of youth justice involvement, the FASD Coordinator should support access to diagnostic pathways, assessments, and service planning in a manner that aligns, where possible, with any custody timelines, diversion programs, or court-ordered services.
c. Provider team identified
A team meeting, with the FASD Coordinator and local cross-sector partners involved with providing support to the child/youth and their family/support network may be required to support the development of the FASD Service Plan. Families/support networks and the child/youth (as appropriate) are critical partners in FASD Coordination Services and should be identified as equal members of the provider team.
With consent from the family/support network and/or the child/youth, the provider team may include service providers from within and beyond children’s services, such as education, health care, youth justice or child welfare. Examples of local cross-sector partners who may be included are:
- CSP Service Planning Coordinators
- Speech and language therapists
- Occupational therapists
- Special education teachers, educators, or other school staff
- Social workers
- Primary care providers
- Psychologists, psychiatrists, or other mental health professionals
- Health care coordinators
- Behavioural therapists
- Probation officers, diversion program staff, and youth justice case workers
Not all professionals involved in a child’s/youth’s services are required to attend the team meeting. Participation should be determined based on the child’s/youth’s needs, the specific purpose of the meeting, and the preferences of the child/youth and family/support network. The family/support network and/or the child/youth will determine which local cross-sector partners should be invited.
Team meetings should be held in locations that are comfortable and accessible for the family/support network. Supports to facilitate participation (e.g., interpretation services, a support person, or virtual conferencing options) should be made available as needed. Families/support networks play a central role on the provider team, as they provide essential insight into their child’s/youth’s interests, strengths, needs, and history, which form the foundation of the FASD Service Plan.
d. FASD service plan is developed
The FASD Service Plan is a written document for a child/youth and their family/support network, as well as all local cross-sector partners involved in their care. At a minimum, the FASD Service Plan will include:
- General information about the child/youth and their family/support network;
- Information about the strengths, needs, and interests of the child/youth and their family/support network;
- Information on whether the child/youth has received an FASD diagnosis, has experienced any barriers to obtaining a formal diagnosis, or would like to obtain a diagnosis;
- The child/youth and family/support network’s vision and priorities (e.g., what is most important to the child/youth and their family/support network and their longer-term aspirations);
- A list of provider team members and agencies involved in providing services to the child/youth, including their roles and responsibilities; and
- Identified goals, how each goal will be achieved, and who is responsible for each action.
Consistent with CSP practices, children/youth should have only one active FASD Service Plan at a time to ensure clear coordination and prevent duplication of services.
The FASD Service Plan should aim to capture all services that are required by, or would be beneficial for, the child/youth. The FASD Service Plan complements individual treatment plans by presenting a holistic view of the child/youth and their family/support network. The goals and vision of the FASD Service Plan should inform, and be informed by, all planning related to services, supports, and special education.
Families/support networks can expect the FASD Service Plan to be a living document that evolves as their child/youth grows and their needs change. The plan belongs to the family/support network, and the FASD Coordinator monitors it on their behalf and works collaboratively with them to update it over time.
The family/support network and/or the child/youth should clearly understand how services are being planned to support the agreed-upon goals. Local cross-sector partners are encouraged to articulate how their services align with and contribute to these goals. Local cross-sector partners determine which services they provide based on applicable policy and program requirements and their areas of expertise.
FASD Coordinators will work with the child/youth and local cross-sector partners to ensure the family/support network has the information needed to make informed decisions about services. FASD Coordinators are responsible for understanding, monitoring, and documenting how services support how prioritized goals may be achieved.
e. Plan is shared with family/support network and providers
Once the FASD Service Plan has been documented, it will be shared with the child/youth and their family/support network. The final decision about who may access the FASD Service Plan, or specific parts of the plan, rests with the family/support network and/or the child/youth.
With consent from the family/support network, the FASD Coordinator is responsible for ensuring that the FASD Service Plan is shared with relevant local cross-sector partners. With appropriate consent, FASD Coordinators are also responsible for communicating information about the child’s/youth’s and family/support network’s needs, strengths, goals, and priorities to local cross-sector partners to support coordinated service delivery.
f. Services and goals are monitored
In addition to maintaining regular communication with families/support networks, FASD Coordinators should inform families/support networks that they may contact the FASD Coordinators at any time if they:
- Have questions about the FASD Service Plan;
- Feel the plan should be adjusted;
- Wish to revise goals;
- Require additional supports; or
- Identify a need for new or different services.
As new needs or potential supports are identified, FASD Coordinators will facilitate referrals and connections and, where appropriate, convene meetings with local cross-sector partners when the family/support network indicates that goals have changed or that the FASD Service Plan requires adjustment. Where possible, FASD Coordinators should contact partners on behalf of the family/support network and facilitate warm referrals. FASD Coordinators should also support local cross-sector partners in applying FASD-informed approaches.
At a minimum, the FASD Service Plan will be reviewed with the child/youth and family/support network every six months. During each review, goals will be confirmed or revised as needed.
Some families/support networks may require more frequent reviews at certain times. The FASD Service Plan should be updated more frequently during periods of transition in the child/youth’s circumstances or services, such as entry into school, transition to secondary school, or transition to adulthood.
Depending on the needs of the child/youth and their family/support network, FASD Coordination Services may vary in intensity over time, and monitoring and review cycles may occur more frequently.
g. Inactivity and/or discharge
Families/support networks may experience periods when they require few or no FASD Coordination Services or may reach a point where the child/youth and/or their family/support network no longer wish to access FASD Coordination Services. In these situations, Coordinating Agencies may categorize the FASD Service Plan as inactive or consider discharge from FASD Coordination Services.
Inactive plans
An FASD Service Plan may be categorized as inactive when there is no immediate need for service, but the family/support network would like the option to re-engage with FASD Coordination Services at a future time.
Plans may be categorized as inactive when there is no need for reassessment, active service planning, or regular review of the FASD Service Plan, because the child or youth and family/support network have effective strategies and FASD-informed services in place.
Before placing the child on inactive status, this should be discussed with the child/youth and family/support network, along with the option to re-engage. FASD Coordinators should advise families/support networks that service engagement is flexible and that they may disengage from and re-engage with FASD Coordination Services as their needs evolve (up to age 18, or 21 if the youth remains in secondary school).
With appropriate consent, the Coordinating Agency should retain inactive files to allow families/support networks to re-engage with FASD Coordination Services, as needed, without having to repeat the intake process.
Prior to categorizing a plan as inactive, Coordinating Agencies may take a coaching approach with families/support networks and other service providers and gradually step-down service intensity. Agencies may also choose to proactively reach out to families/support networks at anticipated transition points (e.g., entry into school, transition to adolescence, or transition to secondary school) to remind them that they may re-enter FASD Coordination Services to receive additional support during these periods.
Discharge
Children/youth are eligible for FASD Coordination Services until the age of 18, or up to the age of 21 if they remain in secondary school. In addition to age-based eligibility, Coordinating Agencies should consider discharge from FASD Coordination Services in the following circumstances:
- Goals have been met, and the child/youth and/or the family/support network and provider team agree that FASD Coordination Services are no longer required;
- The child/youth and/or family/support network move out of the service catchment area, within Ontario. With appropriate consent, the Coordinating Agency should provide a warm referral and share the current FASD Service Plan with the Coordinating Agency in the new catchment area. The family/support network should not be required to undergo another intake process;
- The family/support network cannot be reached after four documented contact attempts over two consecutive quarters, using the preferred method of contact identified by the family/support network (families/support networks are expected to keep current contact information on file with the agency while receiving services);
- The child/youth and/or family/support network request discharge; or
- The possibility of FASD has been ruled out, and the child/youth and their family/support network are referred to other appropriate services for which they are eligible.
Once a child/youth has been discharged from FASD Coordination Services, FASD Coordinators should notify relevant local cross-sector partners involved in their care. This supports cross-sector partners’ awareness that no further action is required.